

Focus On The COVID-19 Death Rate Tyler Durden
Tue, 05/26/2020 – 09:50
Authored
by Gregory van Kipnis via The American Institute for Economic
Research,


In the saga of the virus and the lockdown, the wisdom of
the crowds, that is the wisdom of each of us, was thwarted by
bad data, perhaps intentionally bad. On the other
hand, the ersatz wisdom of the collective bureaucracy in federal,
state and local health agencies was based on crafted data. In the
end data didn’t matter, as the bureaucracies were more concerned
with their natural territorial imperative, which is to rule and
control.
The most frightening aspect of the coronavirus-19
(COVID-19) epidemic in the US is that it brought about
exaggeratedly heightened fear of death. That fear, once magnified
to proportions which become palpable to the individual, became the
basis for dreadful economic and medical policies from governments
and crushed the natural optimism of the public.
In early days, we were caught in a squeeze of conflicting
information. Was COVID-19 a bioweapon gone rogue and destined to
indiscriminately wipe out young and old? Or, was it another bad flu
or perhaps an extremely bad flu? After all, initial information
showed the victims were concentrated in a nursing home in Kirkland,
Washington.
No cases were reported amongst the homeless on West
Coast streets. No deaths among children were reported. And in the
closed world of cruise liners and later a military ship, there were
lots of early cases and some deaths. As time passed, there was
little more bad news. We should have been suspicious of the
data.
We were mainly focused on the case fatality rate (CFR: deaths as
a percent of diagnosed cases) which were frighteningly high. We
worried about the infection fatality rate (IFR), but there was too
little data and testing available to have any idea how many people
were or ultimately would be infected.


But those concepts – CFR and IFR – are not the most
important strategic measures of the severity of the disease. It is
the death rate, properly defined and understood, that should matter
for long-term policy makers, our erstwhile more level-headed
thinkers, in determining policy.
In the past few weeks, we have obtained more useful data
in the US. There were secrets lurking in the data, waiting to be
uncovered, that could help ascertain what was really
happening. The purpose of this report is to do just that
– to ascertain what the data are telling us. It also gives us the
basis for judging the appropriateness of past and present
policies
So, let’s begin with a simple question: what is the relevant
death rate due to COVID-19? There are many definitions in the
epidemiological world such as the CFR and IFR mentioned above. My
focus is on the overall death rate – actual and projected. Until
we have more widespread testing for COVID-19, we cannot know with
any accuracy how many people were infected by the virus. We cannot
know what proportion of the population has some sort of natural or
acquired immunity.
We do not even have accurate data on how many people have died
from COVID-19 alone versus COVID-19 plus some other complications
that were already present such as diabetes, morbid obesity and
prior respiratory complications, any one of which might equally
have been the proximate cause of death. There is ample evidence,
especially in the Northeast region that there has been “over
classification†(a euphemism for data bias). We do not have the
demographic details for those infected and those who died. But we
do have death data, and it is more accurate than the number of
cases and the number of infections.
To understand how our minds have been misdirected in
understanding the real risks associated with COVID-19, let’s
begin with a brain teaser. It will awaken our numerate minds in
preparation for understanding the data deception and
misunderstandings that prevail.
When is 1.7% greater than 98.3%?
In the bizarro world of COVID-19 reporting that is the
case – 1.7% is greater than 98.3%. Specifically, deaths
among a narrow 1.7% group of the population are greater than deaths
from the other 98.3%. Numerically a death may be a death, but from
a policy point of view, to be blunt about it, not all deaths are
the same.
Fact #1: 1.7% of the population in the US resides in long-term
medical care facilities (LTMCFs) and total 5.7 million.Fact #2: The residents of LTMCFs accounted for 38,800 or 53% of
all COVID-19 deaths (based on recent data). The rest of the
country, the 98.3%, have experienced approximately 34,600 deaths,
or 47% of the nation’s total COVID-19 deaths.
The Death Rate at LTMCFs Is Stunning
That means the death rate, deaths expressed as a percent
of those living in medical care institutions, is 0.682%, more than
50 times the death rate of the rest of the population at 0.012%.
The death rate for the overall populations is 0.022%.
That should leave you speechless.
We have a COVID-19 problem, but we have an even greater and more
serious LTMCF problem that is clouding our understanding of the
contagion and therefore what our best public health policies should
be. Shutting down the economy, the world wherein the 98.3% live and
prosper was too draconian. The feared overloading of the hospital
system with emergency patients, which was short-lived, was
disproportionately coming from the residents of LTMCFs, not the
general public.
The data have been there all along, but they were not properly
collected, catalogued and analyzed.
Much of the data in this report came from a landmark
study by Gregg Girvan and Avik Roy of the Foundation for
Research of Equal Opportunity. Their work was based on data
collected through May 10th, 2020 for most states. Since their
publication, revisions have been incorporated as states have
corrected or updated their data since the original report. The
calculations given above are imputations from the updated
data.
At this point, we do not know what the ultimate count of deaths
and the death rate will be, but what we have in hand are statistics
that are very indicative and telling of the gross misunderstanding
that the public and federal, state and local decision-makers have
been working with on which to base their decisions.
Long-term medical care providers to the aged and medically
infirm (per the Girvan-Roy study) consist of: Nursing homes
and skilled nursing facilities; Assisted living facilities, i.e.,
residential care communities or personal care homes; Adult day
service centers; Home health Agencies; and Hospices.
The first two medical care providers for seniors are referred to
as long-term medical care facilities (LTMCF) and are the source of
the data. Data for the other three elder care facilities are not
collected or were not available for the Girvan-Roy study. In fact,
it has been acknowledged that there continues to be underreporting
of deaths related to LTMCFs. Some providers are just not reporting.
In other cases, the residents die in hospitals and they are not
categorized as LTMCF deaths. Nonetheless, the data are sufficient
to draw some useful if not stark observations.
What about the Flu and Pneumonia Death Rates in Earlier
Years?
To even better understand these death rate figures, it is useful
to put them into the context of what we know about death rates from
the flu before the arrival of COVID-19. Is the COVID-19 death rate
worse, better or about the same as prior flu seasons? We should
expect the rates to be worse because there is no vaccine whereas
most people get a vaccine shot for the routine flus that are
expected each year.
In 2017 the Centers for Disease Control (CDC) reported that
annual deaths from all causes were 2.8 million or 0.866% of the
population. The leading causes of death, in order of magnitude,
were heart disease, accidents, respiratory disease, stroke,
Alzheimer’s disease, diabetes, flu & pneumonia and
suicide.
Just looking at the Flu & Pneumonia (FP) cause, in
2017 it accounted for 55,672 deaths or 0.017% for the
population as a whole. Death from FP, as you would expect, fell
hardest on people over 75 totaling 38,078 deaths. That translates
into a FP death rate of 0.180% for those over-75 group, which is a
little more than 10 times the death rate for the overall
population. For the rest of the population under 75 the death rate
was only 0.006%, or 30 times greater than those over 75.
DEATH RATE FOR COVID-19 AND THE FLU FOR SELECTED
DEMOGRAPHICS
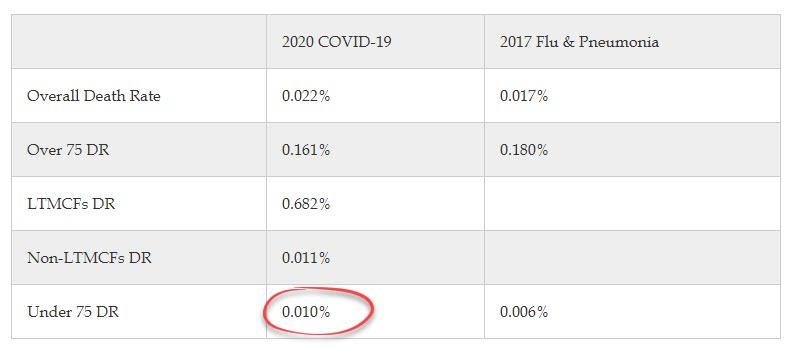
What this means at this point is that in the aggregate the
overall COVID-19 death rate is slightly worse than the flu death
rate in a prior year (0.022% vs 0.017%). However, for seniors in
LTMCFs, the COVID-19
death rate is 100 times greater than the flu and pneumonia DR
was for those over 75 in 2017.
In summary the COVID-19 death rate is far more skewed to
those older than 75 and those residents in medical care facilities
for the aged.
What Does the Future Hold?
Looking ahead we obtained the most recent forecast from the
Institute for Health Metrics and Evaluation (IHME) at the
University of Washington. They are considered by many medical
professionals as the most thorough modelers. On May 18, 2020 the
IHME released the results of the third run of its new model. They
predict that by August 4, 2020 a total of 143,357 Americans will
die of COVID-19. That forecast nearly doubles the number of
COVID-19 deaths. It is worth noting that each run of the
model has produced lower forecasts for future deaths. There are
detractors of their modeling procedures, but it is the best we have
at the moment.
One interesting medical research report suggests that a
significant portion of the population has natural immunity to
COVID-19. In the May 14
edition of Cell, published by Elsevier, the researchers
found:
T cell responses were detected in 40-60% of unexposed
individuals. This may be reflective of some degree of
cross-reactive, preexisting immunity to SARSCoV-2 in some, but not
all, individuals… suggesting cross-reactive T cell recognition
between circulating ‘common cold’ coronaviruses and
SARS-CoV-2.
This might be why there are so many reports of asymptomatic
cases of COVID-19. That also may mean the IHME forecast will be
revised down even more.
However, COVID-19 has brutal consequences for people
over 75. That detail cannot be minimized. But what policies would
that suggest?
Did We Adopt the Right Policies?
What do these data suggest about the medical and economic
policies that have been adopted by the federal, states and local
governments?
The carnage of COVID-19 is concentrated in elder care
facilities not in the population at large. The policies and
procedures, including lockdowns and state-of-the-art personal
protection practices for those facilities, should have been more
thoroughly thought out based on useful data.
Keep in mind, about 70% of the elder care facilities are
for-profit. Yet they are not free-market enterprises; enterprises
free to do what they think is best. These for-profit facilities are
licensed and regulated by the several Departments of Health of the
states. They do what the state tells them to do.
The governors and mayors, and their medical and science
advisers, made the decision to pack them in, force them to house
and retain infected and returning infected patients. They chose to
divert PPE supplies to hospitals, not the elder care facilities.
This characterization is based on reports in the press. One
certainly hopes there were some communities that did a better job.
There is reason to believe that is the case because some assisted
living facilities have reported no deaths.
As COVID-19 deaths mounted, not a word was officially
spoken about where they were occurring. Fear was stoked that it was
a population-wide epidemic. We should ALL lock down.
What a costly mistake, a mistake that continues to this day.
Governors and mayors with fresh data insights into the truth still
want to be central planners and determine which businesses can
re-open and to what degree, who should still shelter or socially
distance. They send out teams to draw circles in the grass defining
where groups can camp out and place police monitors in all the
parks to warn people to stay within the circles. At this point they
are just imaginary prisons, but they are prisons.
Madness, sheer madness.
Though that is an easy and superficial observation to make, what
is really unsaid, and not easy to admit, is that large numbers of
politicians and bureaucrats have revealed their true nature.
Speeches decorated with declarations of “better safe than
sorry†and “planning is better than no planning†reveal they
are authoritarians by nature; central planners of the worst
kind.
In conclusion, the relevant death rate for policy
purposes has been obscured. The consequence has been
inappropriate policies. They have resulted in a bizarro
world of highly restricted commercial functioning and immense
economic destruction, alongside no evidence that lives were saved
and growing evidence of second-tier loss of life resulting from
lockdown.




